HIV Patient Diagnosed with Secondary Syphilis After Unprotected Sex
A 48-year-old HIV-positive man with well-controlled viral load was diagnosed with secondary syphilis after unprotected sex, confirmed by blood tests showing positive RPR and treponemal antibody results. He was treated with penicillin inject
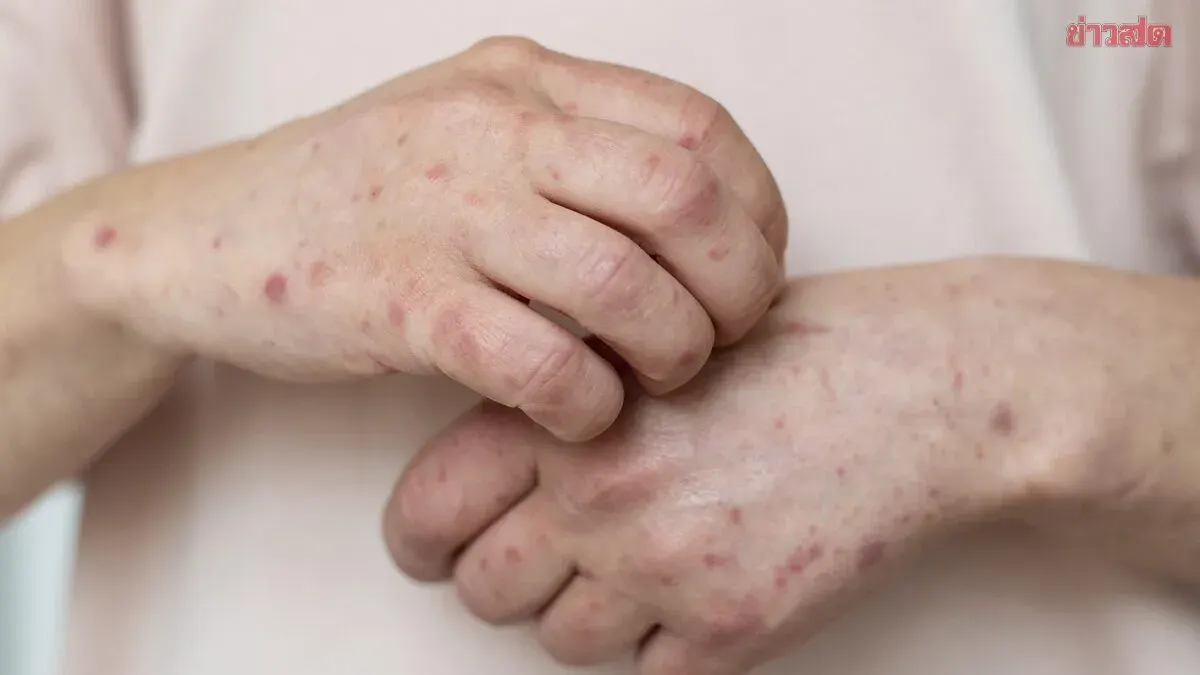
On September 22, 2569, Dr. Monoon Leechaiwongwong, a respiratory physician specializing in severe patients, elderly patients, and lung and infectious diseases at Vichai Yuttho Hospital, presented an interesting case through his Facebook page. The patient is a 48-year-old Thai male with a red rash on his trunk, arms, and upper legs that has been itchy for about one week. He has no fever and no oral ulcers. He reported having unprotected sex two months prior. The patient has a history of HIV infection and has been on continuous antiretroviral therapy for 11 years with good viral control.
Physical examination showed no fever, with a red rash on the trunk, arms, and legs, but no rash on the palms, soles, or swollen lymph nodes. Blood tests showed positive RPR (reactive 1:32, previously negative 10 and 7 years ago) and positive Treponemal Antibody testing, confirming secondary syphilis.
Treatment consisted of Benzathine penicillin G injections into both buttocks (1.2 million units each). Six hours after injection, the patient developed fever, body aches, and increased rash, but improved within 24 hours after taking paracetamol. These symptoms resulted from a Jarisch-Herxheimer reaction, which typically occurs 2-8 hours after the first penicillin injection and resolves within 24 hours. The penicillin rapidly kills the syphilis bacterium (Treponema pallidum), and the dying bacteria release substances into the bloodstream that trigger an inflammatory response, causing fever, chills, headache, and muscle pain, which temporarily worsens the existing rash.
Thailand has experienced a continuous increase in syphilis cases, particularly among youth and adolescents. Secondary syphilis typically presents with body rash, especially on palms and soles, which is usually non-itchy, accompanied by swollen lymph nodes or low-grade fever. This patient presented atypically with no fever, minimal itching, no rash on palms or soles, and no lymph node enlargement, but syphilis was confirmed through positive blood tests for both RPR and Treponemal antibody.









